Friday, June 19, 2020

Men's Average Age And Education Level At Birth Of First Child

From The Wall Street Journal, "Why Some Men Delay Fatherhood: First-time fathers are now more than 27 years old, on average; lengthening transition to adulthood is one reason" by Jo Craven McGinty:
The National Center for Family and Marriage Research, where Dr. Guzzo is an affiliate, analyzed the education, relationship status and average age at fatherhood among men ages 40 to 44 using data from the National Survey of Family Growth.

A potential reason for the delay in fatherhood, the researchers found, is what demographers call the “lengthening transition to adulthood”—the point at which men (and women) feel as if they’ve achieved adult status.
Source: The Wall St Journal

Thursday, May 7, 2020

Coronavirus Outbreak In New York City Became The Primary Source Of Infections Around The United States

From The New York Times, "Travel From New York City Seeded Wave of U.S. Outbreaks: The coronavirus outbreak in New York City became the primary source of infections around the United States, researchers have found." by Benedict Carey and James Glanz:

Source: The New York Times
New York City’s coronavirus outbreak grew so large by early March that the city became the primary source of new infections in the United States, new research reveals, as thousands of infected people traveled from the city and seeded outbreaks around the country.


Thursday, April 30, 2020

One-Third Of COVID-19 Hospitalized Patients Show Signs Of Delirium: Best Practices Not Used In The Turmoil

From ScienceBlog, "One-Third Of Hospitalized COVID-19 Patients Show Signs Of Delirium", April 27, 2020, Harvard University:
... [Harvard Professor] Sharon Inouye ... developed a [delirium] program that hundreds of hospitals have used to reduce cases of the condition by an estimated 40 percent.

... best practices for reducing delirium risk are getting lost in the turmoil of COVID-19 care.

Early data from peer-reviewed studies suggest that one-third of hospitalized COVID-19 patients of all ages, and two-thirds of those with severe disease, show signs of delirium, said Inouye. ...

... patients who experience delirium in the hospital remain hospitalized longer than their peers, have more complications and are more likely to die during their hospital stay or in the following year, need long-term care or develop cognitive impairment, including dementia.
***
... overuse of chemical restraints such as antipsychotics and other sedating drugs. ... when a patient starts to get agitated, providers get scared for the patient’s safety and their own safety and feel they have to sedate the patient. But sedating them is not always needed and leads to many complications. [Emphasis added.]

Wednesday, April 29, 2020

Decline In Healthcare Spending Caused Half The Drop In First-Quarter GDP: The Irony Of Crowded Hospitals, Overworked Doctors And Much Less Healthcare For Everyone Else

From The Wall Street Journal, Real Time Economics, "Newsletter Special Edition: The Expansion Is Over" by Jeffrey Sparshott:
Personal consumption of services was less than 30% of GDP in 1957 and 1968. Services now dominate our economy, contributing 47% of GDP last year, and they have borne the brunt of social distancing. Services consumption, from travel to restaurants to doctors’ visits, tumbled 10.2%, annualized, in the first quarter, accounting for roughly all the net decline in quarterly output. Unlike goods, services can’t be stored in inventory and are seldom imported, so almost every dollar not spent on services comes straight out of Americans’ incomes. —Greg Ip
***
Perhaps surprisingly, healthcare spending accounted for nearly half the drop in first-quarter GDP. Yes, the world is in the middle of a healthcare crisis. In all likelihood, consumers are putting off—or unable to schedule—elective and other apparently nonurgent procedures.
Source; The Wall St Journal, Real Time Economics

Tuesday, April 28, 2020

As Many Extra Non-Covid Deaths As Covid Deaths Occurred During Height Of Epidemic: Did Hospitalization Restrictions On Treating Non-Covid Illnesses, Social Isolation, Job Losses And Business Closures Increase Deaths?

A Washington Post article (excerpted below) indicates that there were an estimated 15,400 excess deaths from March and through April 4, only half of which are attributable to Covid-19.

From The Washington Post, "U.S. deaths soared in early weeks of pandemic, far exceeding number attributed to covid-19: An analysis of federal data for the first time estimates excess deaths -- the number beyond what would normally be expected -- during that period." by Emma Brown, Andrew Ba Tran, Beth Reinhard and Monica Ulmanu:

Source: Washington Post
In the early weeks of the coronavirus epidemic, the United States recorded an estimated 15,400 excess deaths, nearly two times as many as were publicly attributed to covid-19 at the time, according to an analysis of federal data conducted for The Washington Post by a research team led by the Yale School of Public Health.

The excess deaths — the number beyond what would normally be expected for that time of year — occurred during March and through April 4, a time when 8,128 coronavirus deaths were reported.

The excess deaths are not necessarily attributable directly to covid-19, the disease caused by the coronavirus. They could include people who died because of the epidemic but not from the disease, such as those who were afraid to seek medical treatment for unrelated illnesses, as well as some number of deaths that are part of the ordinary variation in the death rate. The count is also affected by increases or decreases in other categories of deaths, such as suicides, homicides and motor vehicle accidents. [Emphasis added]

Monday, April 27, 2020

Coronavirus Data Is Missing A Baseline Mortality Rate For Those With And Without Covid-19

My posted comment to The Wall Street Journal, "Do Lockdowns Save Many Lives? In Most Places, the Data Say No: The speed with which officials shuttered the economy appears not to be a factor in Covid deaths." by TJ Rodgers:
The data is missing a baseline comparison. For a long time, the only people tested were those who has [had] symptoms similar to Covid-19, fever, etc. The number of Coronavirus cases of those tested is about 19 percent. The overall US death rate of those who tested positive is about 5.5 percent. Old people with secondary illnesses are the bulk of the 5.5 percent deaths. The symptomatic 81 percent, the negatives, did not have Covid-19. What was their death rate? Did seniors with secondary illnesses who tested negative for Covid-19 die at the same or greater rate than those who tested positive for Covid-19? We do not know. If the death rates of ill seniors with and without Covid-19 are not substantially different, why the hysteria and focus of all our attention on the Coronavirus? For example, seniors can die of pneumonia. Is there a difference if it is Covid-19 pneumonia or not a Covid-19 pneumonia? Probably only for politicians, mass media and medical reimbursement.

Tuesday, April 21, 2020

Did Epidemiologists Grossly Underestimate The Public's Willingness And Ability To Reduce Daily Social Contacts?

From Gallup, Gallup Blog, April 21, 2020, "Americans' Social Contacts During the COVID-19 Pandemic" by Jonathan Rothwell:
Adults practicing social distancing generate at least 90% fewer contacts per day than those who are making little effort to social distance, according to new Gallup data. Those who completely or mostly isolate themselves generate about five contacts per day, compared with an average of 52 for those not attempting to isolate themselves.
***
Yet, closing workplaces may not be the only way to mitigate contact and suppress viral transmission. Workers who visit their work site but have made changes in how they do their job reduced contacts by 29% to 69%.

Why Measuring Contacts Matters
In epidemiological models, social distancing has large effects on expected infection growth. Yet, different modeling teams have used varying assumptions for the efficacy of social distancing when it comes to reducing contacts. Getting these estimates right would thus appear crucial to accurately understanding the risks and rewards of different mitigation policies.

For example, in research published by public health scholars at Columbia University (PDF download), these scholars have assumed that social distancing can reduce at most 40% of daily contacts. An influential model from Imperial College London defined "social distancing of the entire population" as reducing workplace contacts by 25%, household contacts by 25%, and social or nonwork contacts by 75%.
***
Only 3% of adults and 4% of workers have not made any attempt to isolate themselves.

Largest State Unemployment Fund Declines: Chart

From The Wall Street Journal, Real Time Economics, "Newsletter: States Burn Through Unemployment Funds" by Jeffrey Sparshott:
And nearly half of all U.S. states have logged double-digit percentage declines in their trust-fund balances since the end of February, the month before the pandemic triggered shutdowns that led to widespread job losses, Sarah Chaney reports.

States use trust funds to pay regular unemployment benefits, while the extra $600 payments recently added for workers laid off during the pandemic are funded through a federal stimulus package.
Source: The Wall St Journal, Real Time Economics

Friday, April 17, 2020

Comparison: 2017-18 Flu Season: 61,000 US Deaths Vs Covid-19 35,500 Deaths: 65+ Seniors Were 83 Percent Of Flu Deaths (50,900, 65+ Flu Deaths)

Will the US and State governments close businesses, order wearing face masks and require social distancing during the next H3N2 Flu epidemic?

From Centers for Disease Control and Prevention (CDC), "2017-2018 Estimated Influenza Illnesses, Medical visits, Hospitalizations, and Deaths and Estimated Influenza Illnesses, Medical visits, Hospitalizations, and Deaths Averted by Vaccination in the United States":
CDC estimates that the burden of illness during the 2017–2018 season was high with an estimated 45 million people getting sick with influenza, 21 million people going to a health care provider, 810,000 hospitalizations, and 61,000 deaths from influenza (Table 1). The number of cases of influenza-associated illness that occurred during 2017-2018 was the highest since the 2009 H1N1 pandemic, when an estimated 60 million people were sick with influenza.
***
... 67% of hospitalizations occurred in older adults aged ≥65 years. Older adults also accounted for 83% of deaths, highlighting that older adults are particularly vulnerable to severe disease with influenza virus infection.
New York State, which has the bulk of US coronavirus cases, has about 51,000 cumulative hospitalizations in total compared to the past 2017-18 flu season national total of 810,000 hospitalizations.

From STAT, a December 22, 2017, article about the severity of that season's H3N2 flu strain and social gatherings spreading the flu, "Happy holidays? Flu season is raging and family gatherings may make it worse" by Helen Branswell:
That means lots of people will be sick over the holidays; lots already are. And the multi-generational family gatherings that are part and parcel of the holidays will fuel the spread of the nasty virus.
***
This year could well be a severe year. The viruses causing most of the illness right now are from an influenza A family called H3N2. Those viruses are especially hard on older people and H3 seasons generally are more severe that seasons when H1N1 or influenza B viruses are dominant.

Unfortunately the H3N2 component of the flu shot is an under-performer, often offering protection that is in the 30 percent range. (The other components more commonly offer between 50 percent and 70 percent protection.) So even people who have been vaccinated may find themselves coming down with flu, [Dr. Daniel] Jernigan said.

Wednesday, April 15, 2020

Private Sector Employment By Firm Size: Chart

From E21, "Covid-19 Accelerates Small Businesses’ Woes" by Allison Schrager:

Source: Manhattan Institute Via E21
... They [small businesses] traditionally were an engine of innovation and job creation, but in recent years they become a smaller part of the economy. They still employ many Americans but not as many as they used to.

Tuesday, April 7, 2020

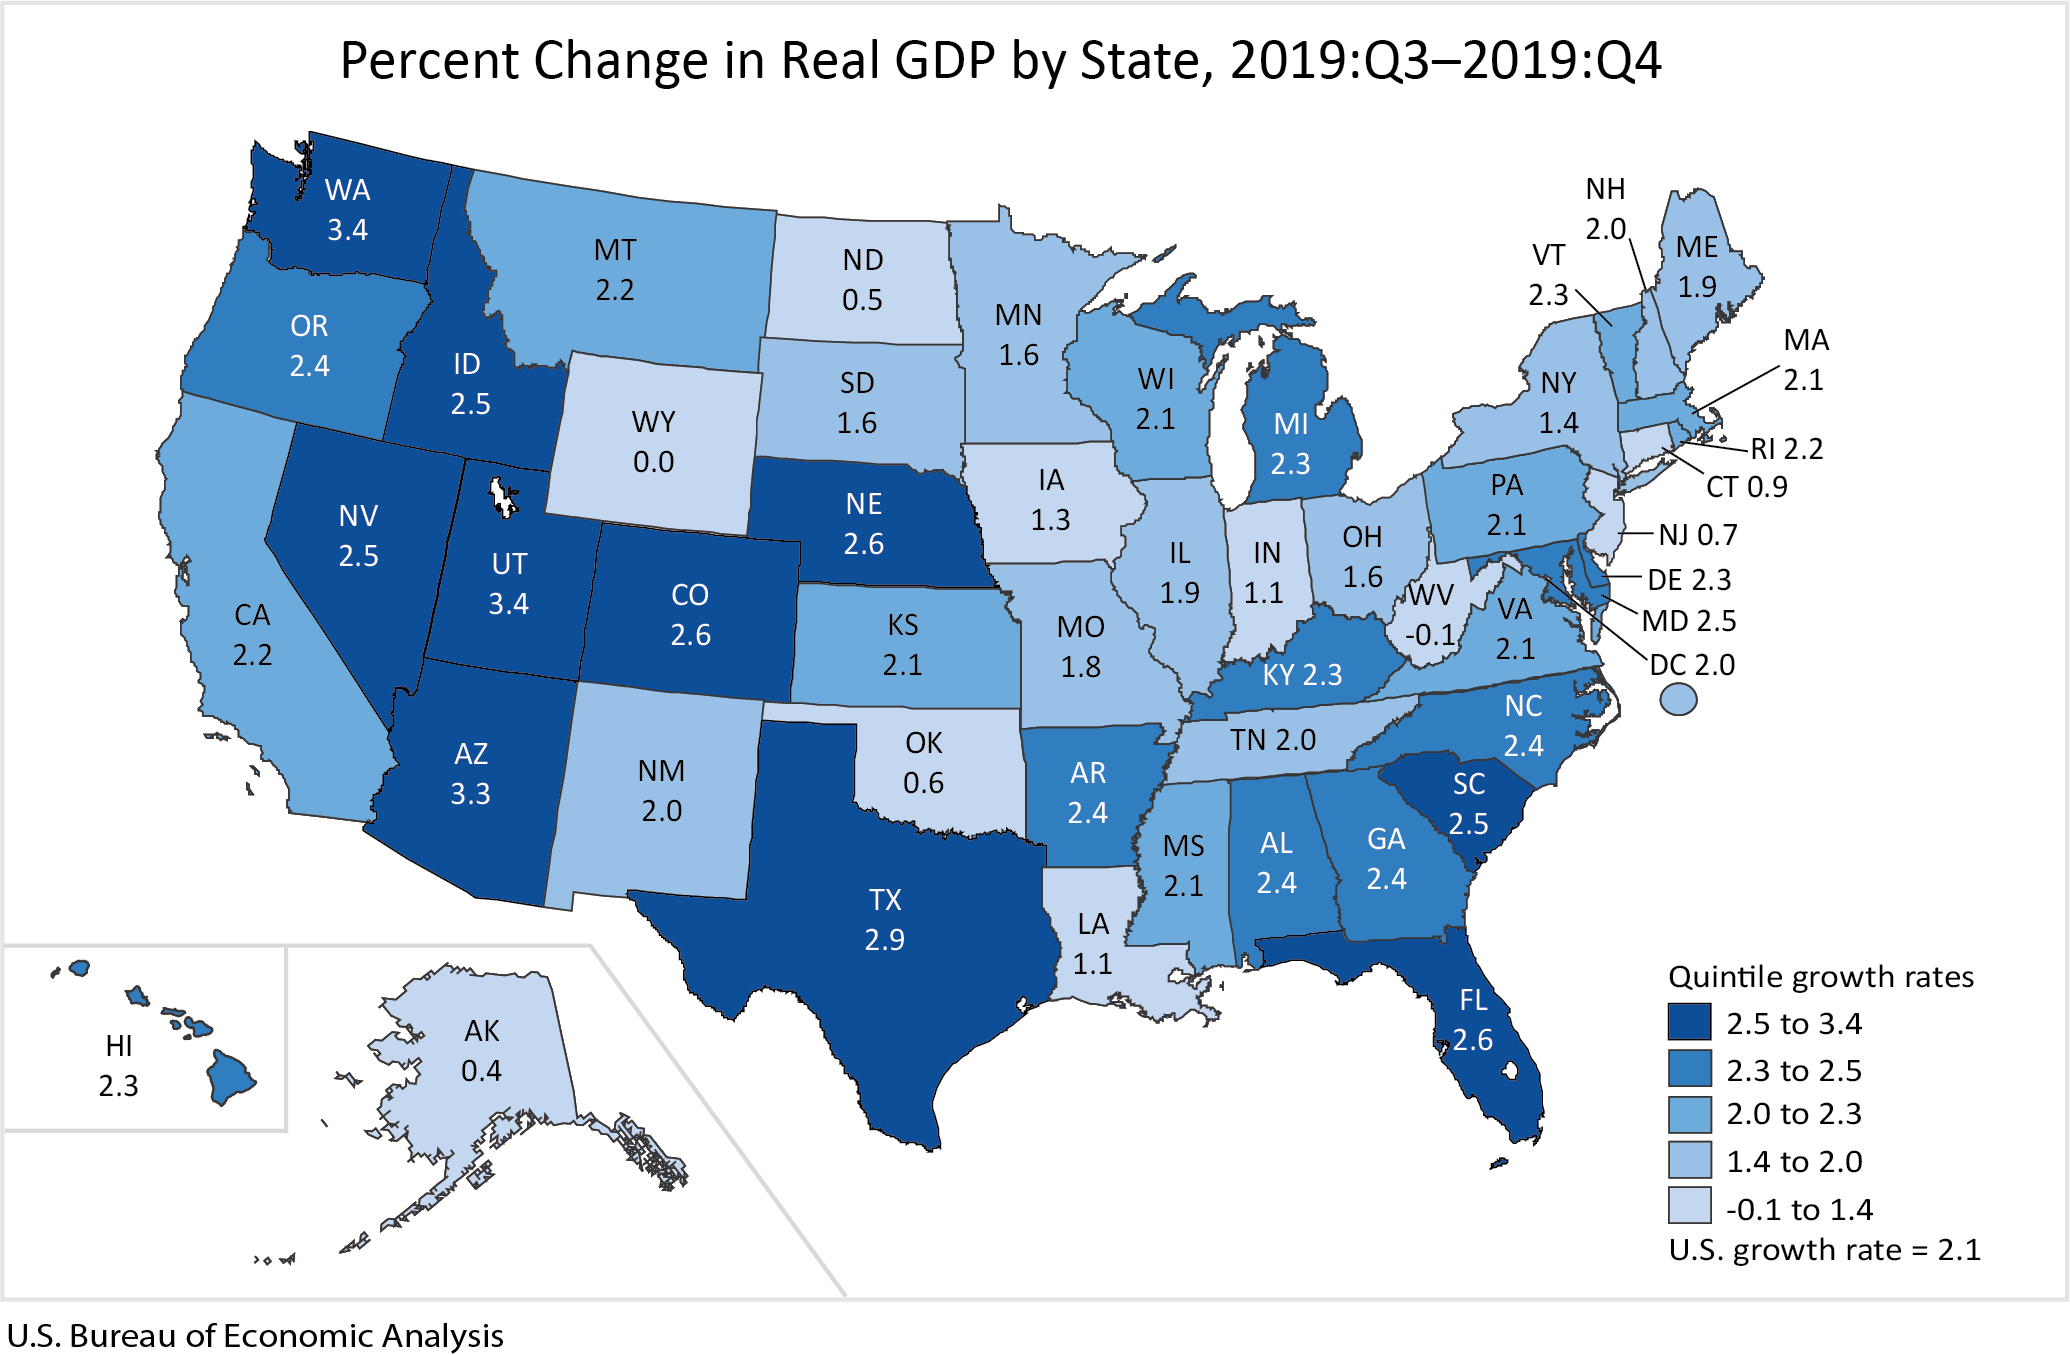
Gross Domestic Product By State: 4th Quarter And Annual 2019

From US Bureau of Economic Analysis, News Release, "Gross Domestic Product by State: 4th Quarter and Annual 2019" (or PDF with tables):
Real gross domestic product (GDP) increased in 48 states and the District of Columbia in the fourth quarter of 2019, according to statistics released today by the U.S. Bureau of Economic Analysis. The percent change in real GDP in the fourth quarter ranged from 3.4 percent in Washington and Utah to -0.1 percent in West Virginia.
Source: Bureau of Economic Analysis

***
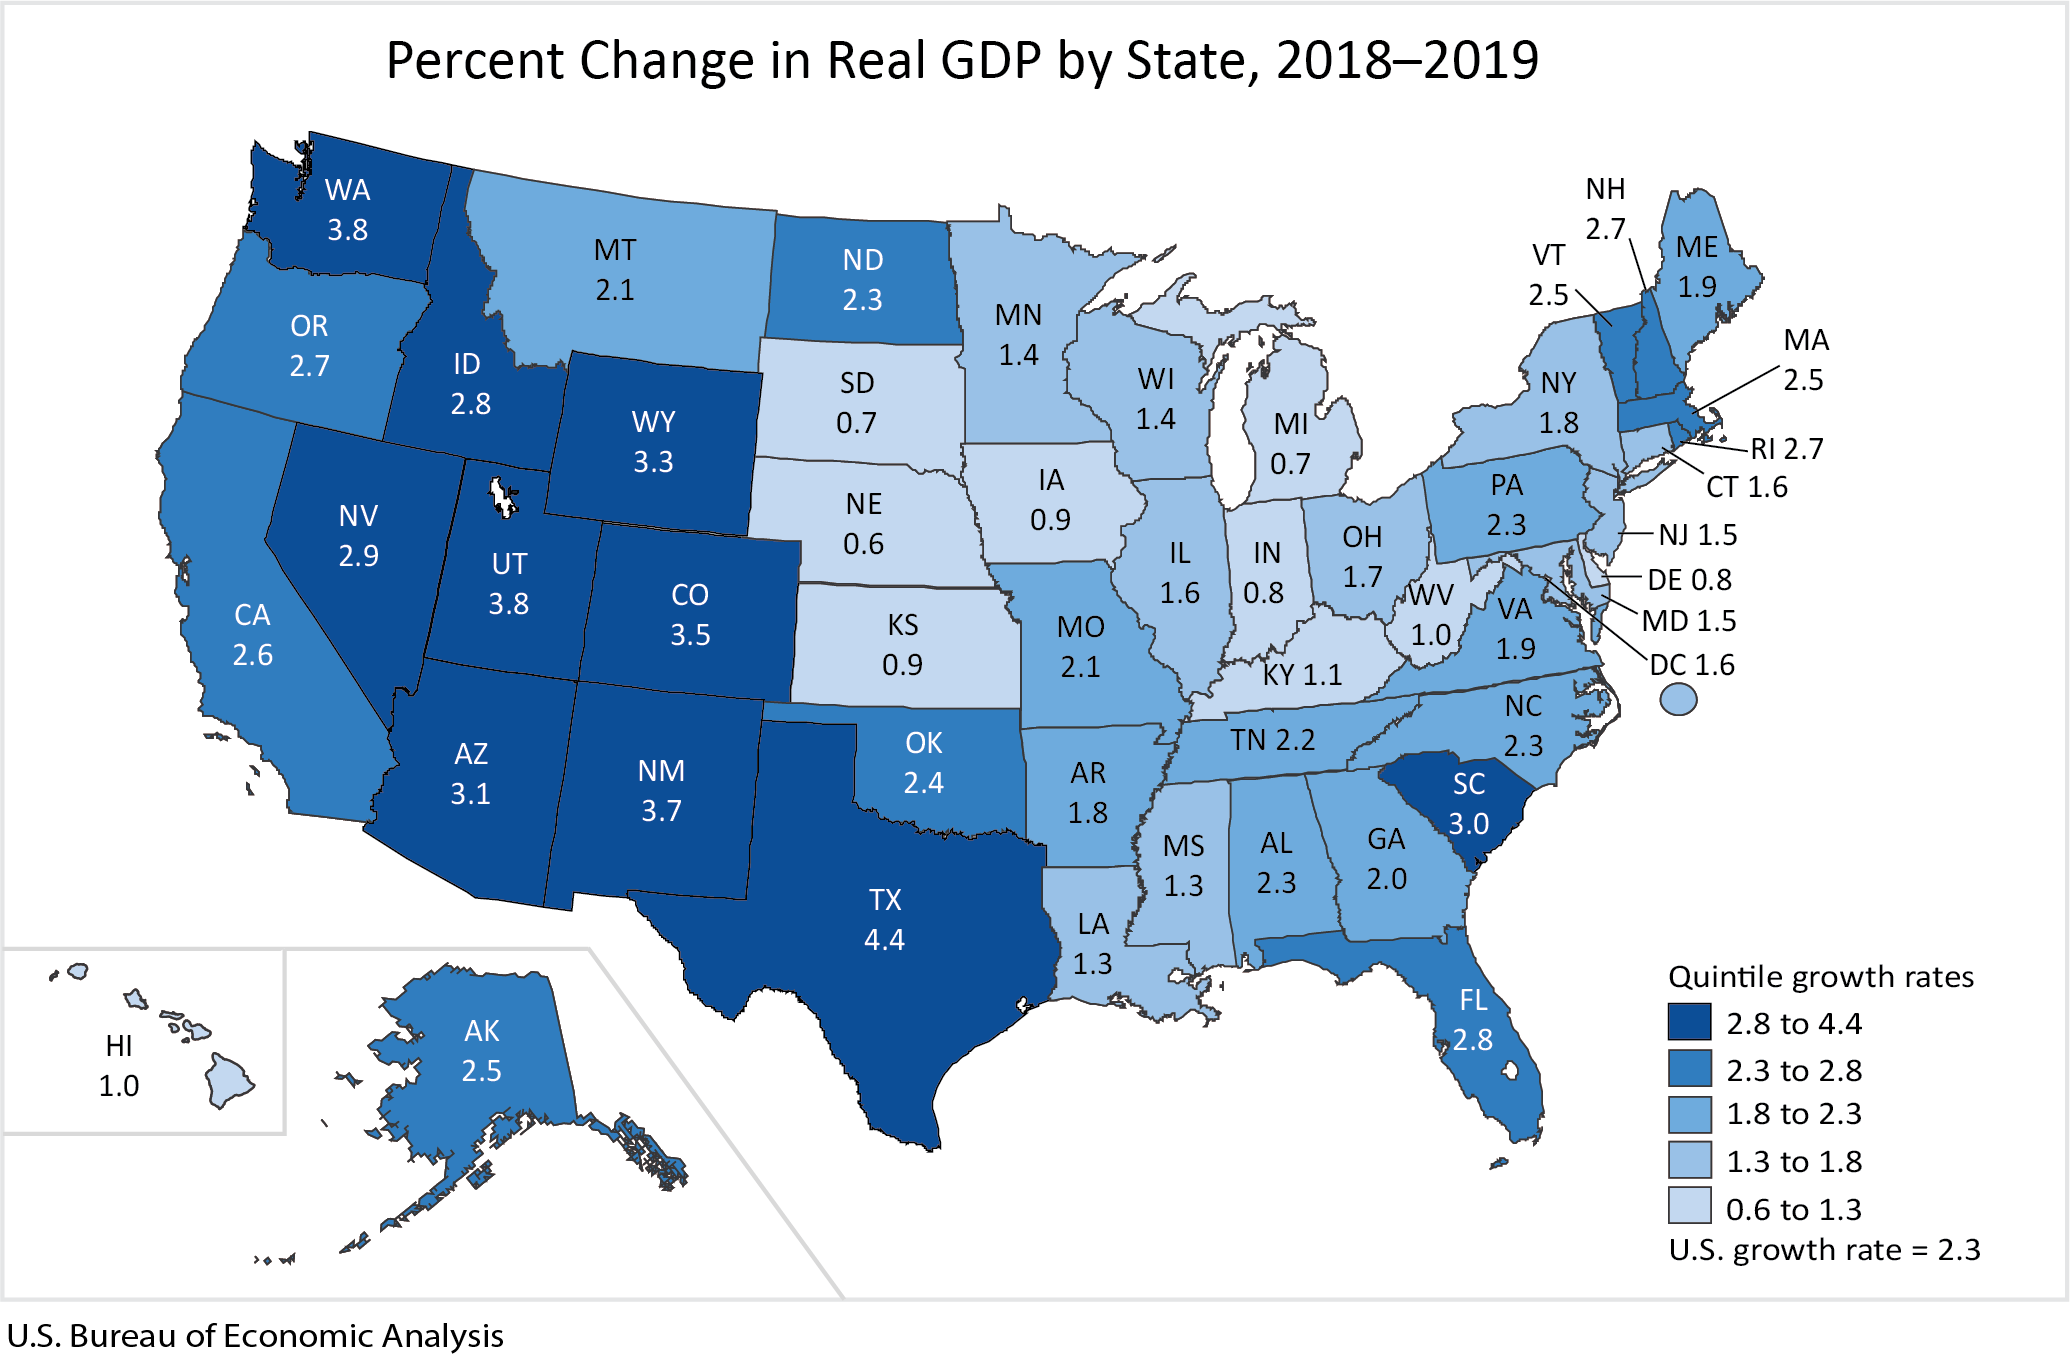
GDP by State, Annual 2019

Real GDP increased in all 50 states and the District of Columbia in 2019. The percent change in real GDP ranged from 4.4 percent in Texas to 0.6 percent in Nebraska.
Source: Bureau of Economic Analysis

Monday, April 6, 2020

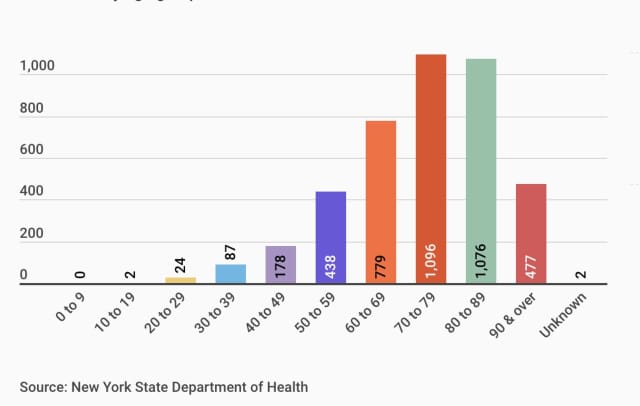
NYS Coronavirus COVID-19 Deaths BY Age Group

From Daily Voice, "COVID-19: New Data On Deaths By Age Group, County Released By New York State" by Joe Lombardi:

NYS Coronavirus COVID-19 Deaths By Age Group
Source: Daily Voice
New data on the number of deaths in New York due to the novel coronavirus (COVID-19) by age group and county has been released by the state health department.

The age group with most of the state's 4,159 COVID-19 deaths is 70 to 79 with 1,096 (26.3 percent). It's followed closely by the 80-89 age group with 1,076 (25.8 percent).

Friday, March 27, 2020

CDC March 21, 2020 Update: 24,000 Influenza Deaths Including 155 Children This Season

From Centers for Disease Control and Prevention, Weekly U.S. Influenza Surveillance Report, "Key Updates for Week 12, ending March 21, 2020:"

Key Points
    ***
  • Pneumonia and influenza mortality levels have been low, but 155 influenza-associated deaths in children have been reported so far this season. This number is higher than recorded at the same time in every season since reporting began in 2004-05, except for the 2009 pandemic.
  • CDC estimates that so far this season there have been at least 39 million flu illnesses, 400,000 hospitalizations and 24,000 deaths from flu.

At the time of publishing this post, there were 100,392 Coronavirus cases and 1,543 deaths in the US. Let's hope deaths from the Coronavirus wil not reach the level of deaths from the Flu.

For the current numbers of Coronavirus cases and deaths:
https://www.worldometers.info/coronavirus/country/us/

Tuesday, March 24, 2020

Unanswered Coronavirus Question

The coronavirus may be a substitution of one cause of death of older, severely ill people for another cause on a death certificate. Stopping the virus might not decrease the mortality rate of the most likely affected individuals.

So far, most of the people dying from the coronavirus are older, have multiple serious health problems and more likely male. On average, an 85 year old male has almost a 10 percent one year mortality rate, a 10 percent chance of dying in one year when not adjusted for the health of the individual, A 90 year old male has a 16 percent chance of dying in one year. Individuals who have multiple serious health problems have much higher mortality rates than the above average actuarial numbers.

The important unanswered question about the coronavirus is whether or not the virus is increasing the mortality rate of severely ill older people? Whether the virus is causing excess deaths in epidemiology terms? If someone is so ill that they would have likely died from heart failure, flu, pneumonia or some other non Covid-19 cause in the next few weeks, dying from the coronavirus and listing it as the cause of death is misleading. It gives the public the false impression that but for the coronavirus the individual would have an extended life and not have died from other causes around the same time.

If stopping the virus does not increase the expected life of infected ill individuals, is it worth shutting down the economy?

Addendum
As more insurance companies modify their existing health insurance policy coverage to fully pay for coronavirus outpatient and in-hospital testing and treatment, doctors will have incentives to list more coronavirus diagnosis as the primary cause of death on medical records and death certificates in place of other causes. The number of deaths due to coronavirus will certainly be inflated by some amount and we should expect to see a sharp increase in proportional deaths around the time of expanded health care insurance coverage.

Wednesday, March 18, 2020

Are We Misreading COVID-19 Statistics? Where Is A Statistical Epidemiologist When You Really Need One? Total Deaths Vs Excess Deaths: Coincident Vs Causal: Contagion Rate Vs Morbidity And Mortality: Aged Adjusted Death Rate

Since death is a natural phenomenon of life, fear of death from a disease, such as the Coronavirus COVID-19, is rational and a major health concern requiring emergency measures, if the virus does the following two things:
  1. Does the virus increase the number of deaths in an age group above the normal mortality rate? In epidemiology terminology: Does the Coronavirus cause Excess Deaths?

  2. Does the virus cause death from various health factors to occur sooner, i.e. shorten life expectancy of an ill person? In epidemiology terminology: Does the Coronavirus cause Premature Deaths?

Excess Deaths
The average US death rate from the known cases of Coronavirus is currently around 1.5 percent, (127 deaths in 8055 Coronavirus cases at the time of publishing this blog post). With many undiagnosed and recovered US Coronavirus cases still unknown, the death rate is likely very much lower than the current 1.5 percent average rate.

Looking at the Social Security Administration Actuarial Life Table for 2016, which is not adjusted for the health of individuals, males have to be 65 years old or older to have a one year mortality rate greater than the COVID-19 average mortality rate of 1.5 percent. Females have to be 70 years old or older to have a one year mortality rate greater than the COVID-19 average mortality rate of 1.5 percent. A 70 year old male has a 2.3 percent one year mortality rate.

At 85 years old, the one year mortality rate is 9.6 and 7.3 percents, respectively. By 90 years old, the one year mortality rates jump to 16 and 13 percents, respectively.

Most of the COVID-19 deaths are occurring in older people who have serious pre-existing health conditions. Their mortality rates are higher, probably much higher, due to their illness than the general population average Social Security actuarial mortality rates.

Absent more detailed contrary statistics from a Statistical Epidemiologist that includes disease mortality rates by age, illness and COVID-19 infection presence, the average Coronavirus data is not showing an excess US population death rate from the virus.

Coincidence Coincident Vs Causality
It appears that the news and our politicians are confusing coincidence coincident with causality.

Imagine a hospital with patients in two wings, Wing A and Wing B, with each section containing severely ill patients with a 50 percent chance of dying within a month. Suppose by chance, the patients in one of the wings, Wing B, get infected with a virus. The staff diagnoses the infection and reports it to health authorities. A few weeks later, the hospital reports to authorities that half the patients in Wing B with the virus died and the others in that wing did not die or get worse.

The news headline would read, "50 percent of hospital patients with the virus died." Without a comparison to the identical, but virus free population, the 50 percent death rate is meaningless. If 50 percent of the patients in the other wing who were not infected with the virus also died, then there are no excess deaths due to the virus. The diagnoses of Wing B patients having the virus infection is a coincident factor. It it something that happened at the same time, but it is not a causal factor, a cause, of any deaths in Wing B.

Coincidence Coincident, and not causality, seems to be the state of our current COVID-19 virus data. We know the virus was present. We do not know it caused the deaths.

Premature Deaths
Looking at the SSA Actuarial Table, one can see that about 10 percent of all 85 year old males and 7 percent of all 85 year old females will die within a year. For a 90 year old, the one year death rate jumps to 16 and 13 percent.

Do we have any reliable data showing that COVID-19 infection has decreased very old senior citizen life expectancy with their already high mortality rates? Probably not.

Since many of the seniors who have died, purportedly from Coronavirus, have been seriously ill, if there were any shortening of remaining life, it may have been, if it occurred at all, for a short time of a few days or a few weeks.

Contagion Vs Morbidity VS Mortality
A high contagion rate is often mentioned about the Coronavirus COVID-19. A highly infectious disease, a high contagion rate disease, means that the disease is easily transmitted from person to person and easily spreads throughout a population. The fact that a disease is easily transmitted, does not indicate that a disease is dangerous nor does it say anything about the effect the disease will have on an individual. The virus infection could have low morbidity. The infection could be innocuous and even unnoticeable with no short or long term effects.

The fact that the Coronavirus is Contagious and has some Morbidity, symptoms, is not an indication that the disease affects Mortality rates. The common cold is highly infectious. It can cause discomfort and generally has a low mortality rate, except for those who have a very high risk for infection, such as immunosuppressed individuals or those who have certain pre-existing health conditions.

Aged Adjusted Death Rates
Comparisons are often made to other countries that are infected with the virus. The percentage numbers will be misleading unless one adjusts for the different percentages in each age group in each country. On the surface, the virus seems to affect different age segments differently. To be able to accurately compare the US to other areas of the world, the numbers for each country's infection and death rate need to be adjusted for different percentages of each population age segment in each country. The process will result in Age Adjusted Death Rates that can be used to accurately compare country death rates.

In a few years, after the studies appear, it will interesting to see if all the extra precautions put into place were warranted or an extreme over-reaction,. We will eventually find out whether the economic harm to the economy and individuals through business and government closings and self-isolation exceeded any harm that may have come form the COVID-19 Coronavirus.

Tuesday, February 25, 2020

Shift Government Focus From The Demand Side Of Medical Care To The Supply Of Medical Care To Lower Health Care Costs

My posted health care cost comment to John Cochrane's blog, The Grumpy Economist, "Health policy wonks and the preservation of human capital":
Shift the focus from the demand side of medical care, i.e., insurance, government subsidies (Medicare for all, Medicaid, Medicare, ACA), and price controls, to a focus on increasing the supply of medical care providers. Lower the barriers to entry for health care providers by lowering the licensing requirements and decreasing the years of education and training it takes to become an independent medical provider. Increasing the supply of medical providers until there is an oversupply will increase competition and productivity. Do the equivalent for hospitals and health facilities. Competition and productivity will remove low quality, high price inefficient providers from the marketplace and lower the costs of medical care. Lower medical care costs will lower insurance costs because insurance is just reimbursement for the cost of the use of medical care. As medical care and hospital costs decrease through productivity, insurance premiums will decline and more people will be able to afford health care. The high cost of medical care and medical insurance is a result of a limited supply of providers and low medical care productivity.

Monday, February 24, 2020

About 5% Of Americans Work More Than One Job

From E21, "Bernie’s Wrong: Americans Now Less Likely to Work 2 or 3 Jobs" by Allison Schrager:
The front-runner for the Democratic Presidential nomination, Bernie Sanders argues one reason the economy is “broken” is that "Millions of Americans are forced to work two or three jobs just to survive."

But the number of Americans working more than one job has actually been declining over the years and is only about 5%. Most multiple job holders have a full-time job and a part-time job. Only 5% of multiple job holders have two full-time jobs. Women are slightly more likely to be multiple job holders.
Source:  E21